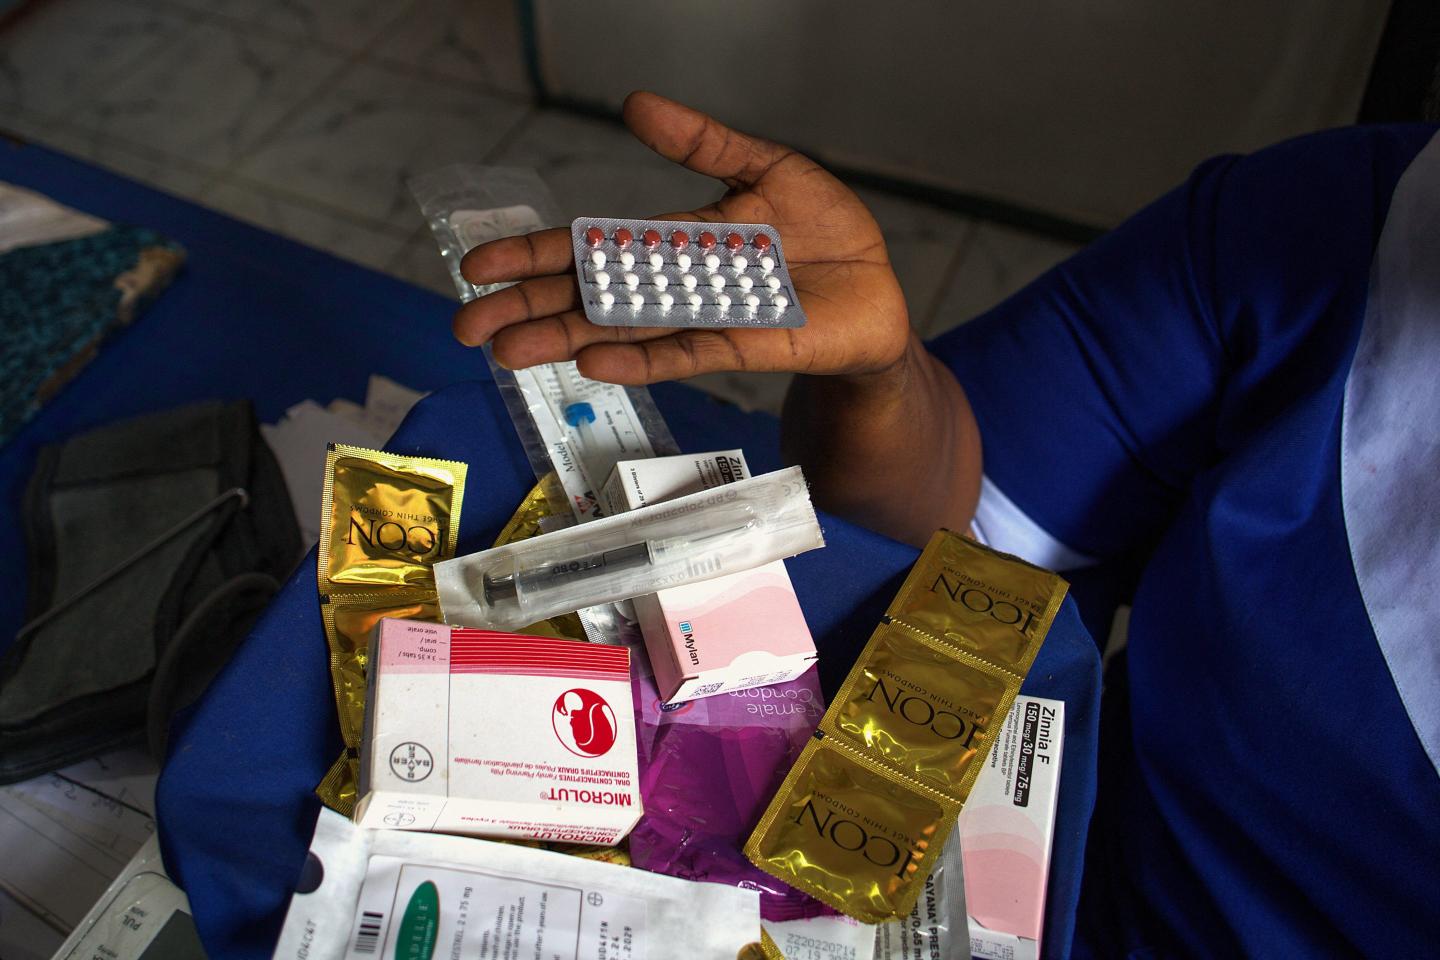
Being a teen mother was far from what Zimbabwean Kelly Nhedega had imagined. The 18-year-old had mapped out a different future: finish school, train as a nurse and then start a family.
But when she became sexually active, contraception felt out of reach. The stigma of a young girl queuing for condoms, pills or a birth control implant at a crowded local clinic where other patients, or even health workers, could judge her or tell her parents, kept Nhedega away. She became pregnant at 16 and dropped out of school.
Now caring for an 18-month-old child, Nhedega recently obtained contraception discreetly as she tries to get back to a classroom.
“That’s a mission I have to complete first. More babies will mean less or no time for school,” she said, her toddler fidgeting on her lap.
As aid cuts and global shipping disruptions threaten access to contraception for girls in Africa, Nhedega’s experience highlights a broader challenge that goes beyond whether contraceptives are being bought or stocked. Parental opposition, restrictive policies, stigma and the fear of being seen at a clinic can stand between girls and contraception, even as governments try to compensate for shrinking foreign aid.
Contraception is critical to helping adolescent girls avoid unintended pregnancies and the risks of childbirth, particularly given Africa’s high maternal mortality rates, experts say.
___
This is part of a series on maternal mortality in sub-Saharan Africa, which has the world’s fastest-growing population and accounts for 70% of global maternal deaths. Around 180,000 pregnancy deaths are recorded every year across the continent.
___
The United Nations Population Fund, or UNFPA, estimates that aid cuts will leave a $185 million shortfall in contraceptive funding globally this year. Nearly 1,400 reproductive health service facilities had closed globally by December, including 1,175 in Africa, leaving an estimated 5.9 million women without services, according to the International Planned Parenthood Federation.
Girls like Nhedega often depend on such basic places for contraception without being scrutinized or exposed. For Nhedega, that place was an aging blue-and-white caravan tucked into a discreet corner of a hospital in Epworth, a densely populated settlement on the outskirts of the capital, Harare. The converted family travel trailer has been transformed into a mobile clinic, giving adolescents a private place to access contraception away from relatives, neighbors, church colleagues or other patients.
“No one will know, it becomes your own secret,” Nhedega said, adding that even after agreeing with her husband to use contraceptives, the community stigma can feel daunting.
Foreign aid support is drying up
Since 2021, the caravan alone has provided more than 100,000 adolescents in Epworth and nearby farming communities and informal settlements with contraceptives, treatment for sexually transmitted infections, counseling and sexual and reproductive health information, said Pester Siraha, director of Population Services Zimbabwe, which operates the caravan and other mobile clinics.
But the service is under pressure as international aid shrinks.
The organization, an affiliate of MSI Reproductive Choices, which provides abortion and contraceptive services in 36 countries, mostly in Africa and Asia, lost a five-year $9 million grant awarded in 2023, after the Trump administration dismantled many aid programs in 2025. Over $6 million of the money was unspent, according to the organization.
It turned to Swedish funding to fill part of the gap, but says that support ended in August, after the Swedish government phased out development assistance to Zimbabwe, Tanzania, Mozambique, Liberia and Bolivia to prioritize Ukraine.
“We were quite excited when Sweden came in,” Siraha said. “Then, suddenly, boom, Sweden said they were leaving,” she said, warning of increased unplanned pregnancies and unsafe abortions that could lead to death.
The funding cuts could force the four-decades-old organization to close its outreach activities. “Or even the entire country program,” Siraha said.
Health Minister Douglas Mombeshora says Zimbabwe has spent $6.3 million buying contraceptives since 2022, and pledged a further $2.25 million a year on contraceptives in 2026 and 2027.
Stigma and consent barriers limit access
But across Africa, availability of contraceptives doesn’t always mean adolescents will get them.
In Zambia, Inonge Wina Chinyama, director at MSI Zambia, said uncertainty over parental consent rules can create an additional obstacle.
“How many young people can go and say, ‘Mommy, I want to have sex tonight. Can you allow me to go and get a contraceptive method?’” she said. “It doesn’t happen in Africa.”
And even girls who navigate through the hurdles may find their preferred contraceptive unavailable at the clinic, she said. Chinyama said the loss of U.S. support for distribution in Zambia was particularly affecting what she called the “last mile” — getting contraceptives from central warehouses and provincial hubs to rural health centers. Contraceptives sitting somewhere in the country are of little use to a girl living far from the warehouse where they are stored, she said.
Global shipping disruptions have added to the uncertainty. In March, UNFPA said carriers have rerouted shipments to avoid conflict-affected waterways. In Zambia, a contraceptive shipment ordered in November arrived more than three months late.
“At first, we thought Zambia was a low-risk country with the Iran war, because it felt like it was very far out there,” said Chinyama. “But we are only just receiving the products this week.”
Big demand for mobile clinics despite aid cuts
In Zimbabwe’s remote communities, the consequences of losing mobile outreach are especially visible, sometimes dramatic.
In Binga, a poor and isolated district in northwestern Zimbabwe, funding cuts forced Population Services Zimbabwe to slow down its mobile clinics. When they briefly returned in August after a six-month absence, girls came running, Engeline Mawere, its operations director, said.
“Sixteen, 17-year-olds, some with children on their backs, were racing toward us when they saw our vehicle,” Mawere said. “Sometimes we park in the bush so that both married and unmarried young girls can feel safe.”
The rush, she said, underlines the importance of outreach services for girls and young mothers. For girls like Nhedega in Epworth, access is not just about what’s on the shelf, but whether they can get contraception without being seen, shamed or stopped.
“So here, you just do it secretly and plan better,” Nhedega said. “There is no child who should be attributed to a mistake. We should be able to plan and decide when to have a baby.”
___
For more on Africa and development: https://apnews.com/hub/africa-pulse
The Associated Press receives financial support for global health and development coverage in Africa from the Gates Foundation. The AP is solely responsible for all content. Find AP’s standards for working with philanthropies, a list of supporters and funded coverage areas at AP.org.